Successful nonoperative management of a simultaneous high-grade splenic injury and devascularized kidney in Australia: a case report
Article information

Abstract
Severe blunt injuries to isolated solid abdominal viscera have been previously managed nonoperatively; however, management algorithms for simultaneous visceral injuries are less well defined. We report a polytrauma case of a 33-year-old man involved in a motorbike collision who presented with left-sided chest and abdominal pain. Initial imaging demonstrated multiple solid organ injuries with American Association for the Surgery of Trauma (AAST) grade V splenic injury and complete devascularization of the left kidney. The patient underwent urgent angioembolic coiling of the distal splenic artery with successful nonoperative management of simultaneous grade V solid organ injuries.
INTRODUCTION
In hospitalized patients, abdominal solid organ injuries are associated with a mortality rate of approximately 5% [1]. Nonoperative management is the preferred approach for stable patients with isolated splenic injuries resulting from blunt trauma [2]. However, simultaneous multiple solid organ injuries are associated with the failure of nonoperative therapy and an increased risk of complications, including pneumonia, sepsis, and prolonged hospitalization [3,4]. Risk factors associated with the failure of nonoperative management include older age, the presence of vascular blush on computed tomography, and a large volume of hemoperitoneum [4]. Additionally, signs of hemodynamic instability including hypotension on presentation, higher Injury Severity Scores (ISSs), and high transfusion requirements are factors associated with a higher mortality rate [3]. We describe below the successful nonoperative management of simultaneous high-grade splenic and kidney injuries following blunt trauma.
CASE REPORT
A man in his 30s presented to our level I trauma center (Westmead Hospital, Sydney, Australia) after being ejected from a motorbike at high speed whilst under the influence of methamphetamines. He was hemodynamically stable, but exhibited confusion and agitation, with a Glasgow Coma Scale of 14. The patient had no relevant past medical history.
An extended focused assessment with sonography for trauma examination was positive for free fluid in the left subphrenic, hepatorenal, and pelvic spaces. Trauma pan computed tomography (CT) demonstrated a large volume of hemoperitoneum, grade V splenic injury, left adrenal hematoma, and a grade V left renal vascular pedicle injury with devascularized left kidney, but no perirenal hematoma (Fig. 1). Other injuries included anterior mediastinal hematoma, bony injuries including right scaphoid and lunate fractures, a left scapula supraclavicular fossa fracture, and an isolated posterior 11th rib fracture. The biochemical markers on presentation were notable for marked acidosis with a venous pH of 7.26 and lactate level of 3.7 mmol/L but a base excess of –1.6 mmol/L. Hemoglobin on presentation was normal (134 g/L), and the patient was identified to be heterozygous for factor V Leiden mutation Arg506Gln (associated with an increased risk of venous thromboembolism [5]).
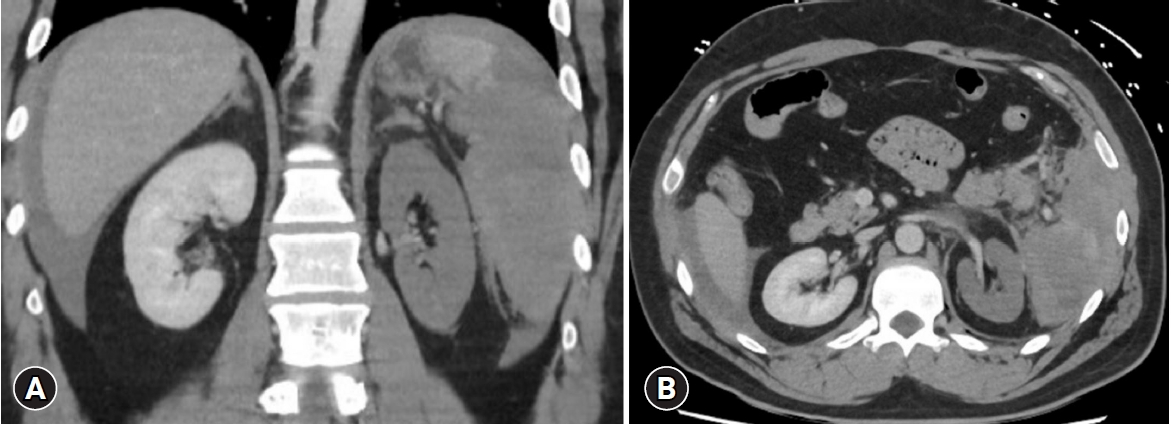
Portal venous phase computed tomography (CT) of the abdomen. On presentation, CT demonstrated large haemoperitoneum, grade V splenic injury, perisplenic haematoma, and a grade V left renal vascular pedicle injury with a devascularized nonenhancing left kidney. (A) Coronal view. (B) Axial view.
The patient was managed with urgent interventional radiology 6 hours after presentation, with a diagnostic aortogram and splenic angiogram demonstrating traumatic dissection and abrupt occlusion of the left main renal artery approximately 2 cm from the renal ostium. No evidence of arteriovenous fistulae or active bleeding was noted. Despite the high-grade renal injury, the renal parenchyma remained intact, and percutaneous stenting was considered as a feasible management strategy. The interventional radiologist was unable to traverse the injury with a wire, and therefore the plan for stenting was abandoned. Significant fragmentation and devascularization of the spleen were identified. Thirteen coils were deployed with additional gelfoam embolization to distal splenic and associated branches beyond the pancreatica magna artery, as shown in Fig. 2. The patient’s scaphoid and lunate fractures were managed with open reduction and internal fixation, while the other bony injuries were nonoperatively managed. The patient was monitored with 6-hourly hemoglobin levels with a trough hemoglobin level of 83 g/L and serial examinations. Chemical venous thromboembolism prophylaxis was commenced 24 hours following angioembolization.
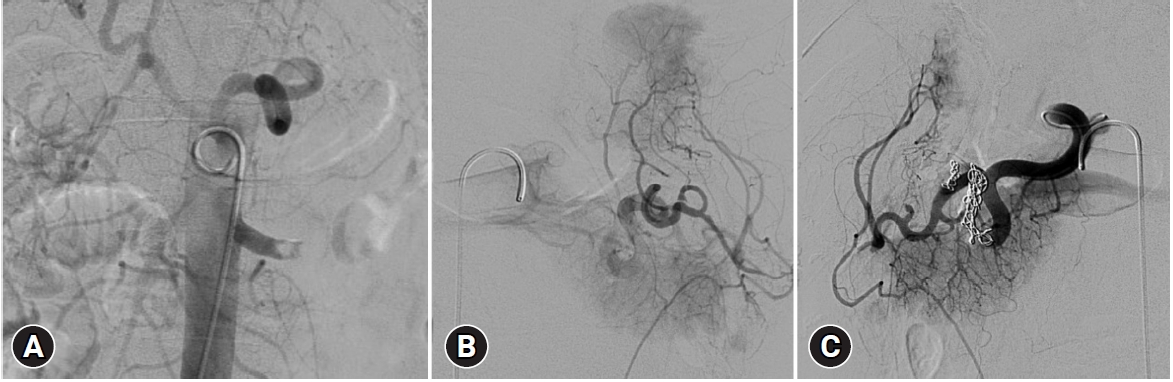
Angiography and angioembolization. (A) Angiography demonstrating traumatic occlusion of the left main renal artery. (B) Significant fragmentation and devascularization of the spleen with small branch vessels supplying shattered splenic fragments without active bleeding. (C) Distal coil and gelfoam embolization to splenic artery and associated branches.
The patient remained hemodynamically stable throughout his admission; however, cyclical high fevers up to 39°C were observed with unremarkable septic screens. Intravenous empirical antibiotics were administered for 7 days after fever commencement. Interval abdominopelvic CT performed 4 and 8 days after presentation demonstrated splenic and left renal infarcts consistent with prior imaging, with no new hematoma formation, pseudoaneurysm, or associated intraabdominal abscesses. Atelectasis was identified on chest imaging. The patient was commenced on patient-controlled analgesia (PCA) and ketamine infusion initially. PCA was discontinued on day 6 posttrauma and de-escalated to only oral analgesia on day 7. He was discharged on day 13, with outpatient follow-up.
Ethics statement
Consent for publication of the research details and clinical images was obtained from the patient.
DISCUSSION
The management of solid injuries is predominantly nonoperative in hemodynamically stable patients, and angioembolization is a useful adjunct to solid organ preservation [6]. The success rates of nonoperative management have been reported to be approximately 86% in splenic trauma [4], 97% in hepatic trauma [7], and 92% in renal trauma [8]. The grading of splenic injuries according to the American Association for the Surgery of Trauma (AAST) Injury Scoring Scale ranges from grade I to V, with grade V referring to splenic and kidney injuries with vascular involvement and bleeding extension into the peritoneum or shattered or devitalized parenchyma. Although some evidence demonstrating a correlation between the failure of nonoperative management and the grade of injury [9], multiple other studies have indicated that nonoperative management is ideal independent of the lesion grade, more strongly for splenic injuries [10] than for renal injuries [9]. Some contemporary recommendations suggest operative management of grade V kidney injuries [6,11,12] depending on hemodynamic stability. In broad terms, however, the risk factors for failure of nonoperative management of solid viscus injuries, including refractory haemodynamic instability and worsening biochemical markers of perfusion (for example, lactate and base excess), reflect the physiologic status of the patient. In this case of a hemodynamically stable patient with no comorbidities, further attempts at renal revascularisation were not pursued. Prolonged ischaemic time is associated with exponential losses in kidney function [11]. An operative intervention was not pursued, as expectant management of sequelae (such as progression to chronic kidney disease or hypertension) during follow-up was considered to have a more favorable risk profile.
Patterns of concomitant solid organ injuries are less well studied and have fewer recommendations for nonoperative management. Important concepts include early recognition with CT imaging [2,13] and serial clinical examinations, with diffuse peritonitis, hemodynamic instability, or persistent biochemical signs of shock despite resuscitation being the only reliable markers of the failure of operative management. Older age, higher ISSs, head injury, the presence of femur fractures, and ongoing blood transfusion requirements are similarly factors that favor operative management and are predictors of failure of nonoperative management [3,4].
This case highlights the successful nonoperative management of concomitant splenic and renal injuries. Solid organ injury management should be dependent on clinical status, with radiology findings determining the role of angioembolization, even in the setting of multiple solid organ injuries.
Notes
Author contributions
Conceptualization: PTTN; Data curation: PTTN; Investigation: PTNN; Methodology: PTTN; Project administration: PTTN; Supervision: HJ; Visualization: PTNN; Writing–original draft: PTTN; Writing–review & editing: all authors. All authors read and approved the final manuscript.
Conflicts of interest
Jeremy M. Hsu is an Editorial Board member of the Journal of Trauma and Injury, but was not involved in the peer reviewer selection, evaluation, or decision process of this article. The authors have no other conflicts of interest to declare.
Funding
The authors received no financial support for this study.
Data availability
Data sharing is not applicable as no new data were created or analyzed in this study.